Daily headaches are a pattern, not something to keep treating one day at a time. Two numbers usually change the conversation.
A headache on most days is a pattern worth investigating. One commonly
missed possibility is that frequent use of headache medication can itself help
maintain the cycle. Start by counting two numbers for the past month:
headache days and medication days. Those two numbers can change what
should happen next.
You don’t really think of yourself as someone with headaches.
You just have one most days.
There’s the bottle in your desk. The one in the car. The one in your bag. You take something in the morning before it gets going, because you learned that if you wait, the day is lost.
Some days it’s a band around your head. Some days it sits behind one eye. Some days it starts at the base of your skull by three in the afternoon and climbs.
You’ve stopped counting.
In fact, if I asked how many days in the last month you had a headache, you would probably
say “a lot.” If I asked how many days you took something for it, you would have to think even harder.
Both of those numbers matter enormously.
Start With Two Numbers
Frequent headaches and frequent headache medication travel together, and the relationship runs in both directions.
When pain relievers are taken often enough, over long enough, the headache pattern can change. Episodic headaches become more frequent, then daily. They start arriving in the early morning. The medication that used to work now works for a few hours before the pain returns, so you take more, which maintains the cycle.
This is a recognized condition. Headache specialists call it medication-overuse headache, or rebound headache, and the approximate thresholds are worth knowing.
• simple pain relievers such as acetaminophen, ibuprofen, naproxen or aspirin, on about 15 or more days per month
• combination pain relievers, migraine-specific medications such as triptans, ergotamines, or any opioid, on about 10 or more days per month
• sustained over roughly three months
Read those numbers, then count your own.
Most people in this pattern have no idea they are in it, because every individual decision made sense. You had a headache. You took something.
Two things follow. This is treatable, and it is managed medically. And coming off the pattern usually involves a period of worse headaches before better ones — which is why opioid and sedative-containing medications in particular must never be stopped abruptly on your own.
So the instruction is not stop your medication. It is count the days, write the number down, and bring it.
The Pattern Matters
Not every daily headache is the same headache. Frequent headaches may reflect migraine, tension-type headache, medication-overuse or rebound headache, a cervicogenic headache arising from the neck, or another cause.
Migraine often brings throbbing pain, nausea, or sensitivity to light and sound, and is made worse by ordinary activity. Many people with migraine have been told for years that they have sinus headaches, because facial pressure and congestion are common features.
A headache with a cervical component may begin in the neck or at the base of the skull, stay on the same side, follow a consistent path forward toward the eye or temple, and change with neck position or sustained posture.
Chronic daily headache is a descriptive term for headache occurring on 15 or more days a month, not a single diagnosis.
The point isn’t to diagnose yourself. It’s to notice the pattern.
The Ordinary Contributors
Sleep, caffeine, skipped meals, hydration, alcohol, jaw clenching, vision, medications, blood pressure, stress and hours spent in one sustained position can all matter. Often more than one is involved.
If your headache is reliably worst on a Saturday morning, that is a clue about caffeine. If it arrives with a new pair of glasses, that is a clue too.
And “it’s stress” is where headache investigations go to die. Stress belongs on the list. It doesn’t belong as the answer.
When a Headache Needs Urgent Attention
A sudden worst-headache-of-your-life, headache with new weakness, numbness, confusion, or speech or vision changes, fever with a stiff neck, or a severe or worsening headache following head injury needs urgent medical evaluation.
A new or steadily changing headache pattern — particularly later in life, or with scalp
tenderness or jaw pain while chewing in an older adult — also deserves prompt medical attention.
What We Can Actually Examine
At Ptak Family Chiropractic in Santa Monica, we start by determining what kind of
headache pattern you have and whether there is a mechanical or neurological component we can identify.
Pain that begins in the neck or base of the skull and travels forward. We examine cervical movement and the upper cervical structures to see whether we can reproduce your familiar headache — not simply find something tender.
Headache brought on by sustained neck position. We examine movement, strength and endurance, and look at the positions and loads that precede the headache.
Measurably restricted neck movement. We determine where movement is restricted and whether changing that movement changes the headache pattern.
A history of whiplash, a fall or neck injury. That changes what we examine and which findings matter.
Numbness, tingling, weakness, balance changes or other neurological symptoms. A neurological examination helps determine what should happen next.
And we count the days with you. Headache days and medication days, both.
What We Find Determines What We Do
There shouldn’t be one treatment for everyone with headaches.
If cervical joint or mechanical dysfunction is relevant, chiropractic and manual care may be useful.
If weakness or poor neck endurance is contributing, strengthening becomes part of the program.
If mobility is restricted, we address mobility.
If sustained position or workload is part of the pattern, we work on changing the load and on improving your capacity to tolerate it.
If neurological findings are present, those findings determine what happens next.
And if our examination tells us your headache belongs with your physician or another
specialist, we’ll tell you and help point you in the right direction.
One honest note about goals. Fewer headache days usually means fewer doses, and fewer doses is often what breaks the cycle. That is a realistic aim. Curing migraine is not.
Bring Four Answers
How many days last month did I have a headache?
How many days did I take something for it?
Where does my headache usually begin?
What reliably brings it on, or makes it worse?
You Are Not Supposed to Have a Headache Most Days
Somewhere along the way this became normal for you. It shouldn’t be.
If you have quietly reorganized your life around it — the bottle in every bag, the appointments you schedule for mornings because afternoons are unreliable, the plans you cancel, the dread when you notice it starting at two o’clock — that is not a personality trait.
It is an unmanaged condition.
Come and talk it through with us. We never charge you to sit down and talk about your needs. Bring the four answers above and your medication list. We will tell you what we think is driving it and what isn’t, and if this belongs with your physician or a neurologist, you will hear that from us that day along with exactly what to bring them.
One conversation, one careful examination, and two honest numbers.
For many people, that is where a daily headache finally starts to make sense.
About the author. Dr. Jeffrey Ptak, DC, DSS, MSS, MA. Bachelor of Science in Psychology, The American University, 1977. Neuroscience research at the Laboratory of Neuropsychology, National Institutes of Health, 1977 to 1980, with peer-reviewed publications in Physiology & Behavior in 1977 and in Catecholamines: Basic and Clinical Frontiers in 1979. Doctoral study in behavioral neuroscience at the City University of New York. Doctor of Chiropractic, Los Angeles College of Chiropractic, 1985 — the professional degree under which he practices. Founder of Ptak Family Chiropractic, Santa Monica, since 1986. Postgraduate study in Chiropractic Functional Neurology through the Carrick Institute, and advanced training through the International Association of Functional Neurology and Rehabilitation. Graduate coursework in Traditional Chinese Medicine at Emperor’s College. Master of Arts in Spiritual Psychology, University of Santa Monica, 2012, and Master of Arts in Spiritual Psychology with an emphasis in Consciousness, Health and Healing, 2016. Master of Spiritual Science, 2021, and Doctor of Spiritual Science, 2025, Peace Theological Seminary & College of Philosophy.
Educational purposes only. This article does not diagnose any condition and is not a substitute for medical care. Do not start, stop or change any prescribed medication without consulting the prescribing physician; some medications must not be discontinued abruptly. Seek emergency care for a sudden severe headache, the worst headache of your life, or headache with fever and stiff neck, confusion, weakness, numbness, slurred speech, vision loss, or headache following head injury. Individual results vary and no particular outcome is promised.
Ptak Family Chiropractic
We listen… We care… We get results…
Chiropractic for Adults and Children
3122 Santa Monica Blvd., Suite 102 · Santa Monica, CA 90404
310.473.7991 · ptakfamilychiropractic.com
Mon / Wed / Thurs 8:00–12:15 and 2:00–6:00 · Tues / Fri 8:00–12:00 · Sat 10:00–12:00
Eight hours in bed and still exhausted? Maybe the question isn’t how long you slept. Maybe it’s whether you actually recovered and whether something is interfering with that.
Sleep and recovery are not the same thing. You can spend eight hours in bed
without getting eight hours of good sleep, and the most useful question is
not how many hours you slept but how you feel when you wake up.
Persistent fatigue has many possible causes, several of them medical. We
don’t treat fatigue. We look for whether something within our scope is
interfering with your ability to sleep comfortably and recover — and what we
find determines what we do.
You went to bed at a reasonable hour. You slept seven hours. Maybe eight.
The alarm goes off, you open your eyes and somehow you feel as though you could sleep for three more.
By ten o’clock you’re already tired. By two in the afternoon you’re looking for another coffee, something sweet, or ten quiet minutes with your eyes closed.
And somewhere along the way you start wondering:
Why am I so tired? I’m sleeping enough.
That is a better question than it may seem. Because sleep and recovery are not the same thing.
Being Asleep Doesn’t Mean You’re Recovering
We measure sleep with a clock. Your body doesn’t. It experiences what happened during those hours.
Was your sleep continuous, or repeatedly interrupted? Were you breathing normally? Were pain or discomfort disturbing you? Were medications, alcohol or caffeine affecting it?
You can spend eight hours in bed without getting eight hours of good sleep.
Which is why the most useful question isn’t how many hours you slept.
It is: how do you feel when you wake up?
If the answer is exhausted, that deserves attention.
Sleepy, Fatigued or Weak?
We use these words interchangeably. They describe different things, and they point in
different directions.
Sleepy means you could actually fall asleep — nodding off reading, or, much more seriously, while driving.
Fatigued means drained without necessarily being sleepy. Heavy, unmotivated, mentally foggy. Your body has energy somewhere, but you can’t get access to it.
Weak means a muscle genuinely cannot produce the force it normally could.
Which one you have changes what should be looked at.
Your Body Has an Energy Budget
Every day your body spends energy — movement, thinking, digestion, temperature, immune activity, healing, and responding to everything asked of it. Recovery is how you replenish the account.
Spend. Restore. Spend. Restore.
But imagine spending slightly more than you restore, every day. Not dramatically more. Just a little.
At first you don’t notice. You compensate. Another coffee. Skip the workout. Sleep later on Sunday. Tell yourself you’re getting older.
A small deficit repeated over months becomes the way you feel every day.
And you stop remembering what rested feels like.
Some of This Isn’t Ours, and You Should Know That First
“I’m tired” is a symptom, not a diagnosis, and a great deal of persistent fatigue is medical: anemia and low iron, vitamin B12 deficiency, thyroid disorders, blood sugar and other metabolic problems, infection, medication side effects, depression and anxiety, nutrition, or recovery from illness taking longer than expected. Those require appropriate medical evaluation, not an adjustment.
Sleep apnea deserves particular attention. Someone can spend plenty of time in bed and still wake unrefreshed because breathing has been repeatedly disrupted. If you snore loudly, someone has noticed you stop breathing, you wake gasping, or you regularly wake with a headache or dry mouth, that needs medical evaluation.
Chiropractic care is not a treatment for any of those conditions, and I am not going to pretend otherwise.
But Here Is What We Can Actually Look For
There is a specific question inside all of this that is genuinely ours.
Is something within our scope interfering with your ability to sleep comfortably and recover?
That is a real question with real findings, and it comes up more often than people expect.
Pain that wakes you, or makes you change position repeatedly. We examine what hurts and which positions provoke or relieve it.
No comfortable position at all. Worth establishing which positions do what, rather than guessing.
Numbness in an arm or hand at night. Position, the neck, or another point along the nerve pathway may be involved, and the pathway can be examined.
Morning headache with neck stiffness. Cervical and neurological findings may be relevant —and so may sleep-disordered breathing, which is why the history matters as much as the examination.
Weakness, poor endurance, restricted mobility or meaningful side-to-side differences. We measure those rather than assume them.
What We Find Determines What We Do
There shouldn’t be one treatment for everyone who is tired.
If spinal or joint dysfunction is relevant, manual chiropractic care may be useful.
If weakness or poor endurance is contributing, specific strengthening becomes part of the program.
If mobility is restricted, we address mobility.
If numbness, tingling or headache accompany the complaint, a neurological examination directs what happens next.
And we give you sleep-position, pillow and home-care recommendations based on your actual pattern rather than generic advice.
What we won’t do is manufacture a chiropractic explanation for a problem that isn’t one. If the history points to anemia, thyroid disease, sleep apnea, a medication effect or another
medical cause, the useful thing we can do is recognize it, tell you plainly, and tell you what to bring to that appointment.
We don’t treat fatigue. We look for whether something within our scope is interfering
with your ability to sleep comfortably and recover — and what we find determines
what we do.
Maybe You’re Not “Just Getting Older”
I hear it all the time. “I guess this is what happens at my age.”
Sometimes age does change recovery. But age should not become the explanation for
everything.
Neither should stress. Neither should being busy. Neither should having children. Neither should menopause. Neither should working too hard.
Those may all contribute. But if you wake exhausted day after day and know your energy is dramatically different from what it used to be, listen to that.
Your body may not be failing you. It may be telling you that something has changed.
Start With a Better Question
Instead of asking:
“How do I get more energy?”
try asking:
“Why am I not recovering?”
Then bring five answers.
How do I feel when I wake up?
Is it sleepiness, fatigue, or weakness?
Does anything wake me — pain, breathing, the bathroom?
Any numbness, tingling or morning headache?
And what changed around the time this began?
You Don’t Have to Settle for Exhausted
Being tired occasionally is part of being human. Being exhausted every day deserves a better explanation.
Come talk with us. We never charge you to sit down and talk about your needs. We’ll take the history, examine what is ours to examine, and tell you honestly whether something we can address is interfering with your recovery. If what you need is laboratory testing, a sleep evaluation or another physician, we’ll tell you that instead — and that answer is worth having too.
Sometimes the beginning of feeling better isn’t another supplement or another attempt to push through.
Sometimes it begins with someone finally asking why you are so tired — and caring enough to keep asking until the picture makes sense.
About the author. Dr. Jeffrey Ptak, DC, DSS, MSS, MA. Bachelor of Science in Psychology, The American
University, 1977. Neuroscience research at the Laboratory of Neuropsychology, National Institutes of Health, 1977 to 1980, with peer-reviewed publications in Physiology & Behavior in 1977 and in Catecholamines: Basic and Clinical Frontiers in 1979. Doctoral study in behavioral neuroscience at the City University of New York. Doctor of Chiropractic, Los Angeles College of Chiropractic, 1985 — the professional degree under which he practices. Founder of Ptak Family Chiropractic, Santa Monica, since 1986. Postgraduate study in Chiropractic Functional Neurology through the Carrick Institute, and advanced training through the International Association of Functional Neurology and Rehabilitation. Graduate coursework in Traditional Chinese Medicine at Emperor’s College. Master of Arts in Spiritual Psychology, University of Santa Monica, 2012, and Master of Arts in Spiritual Psychology with an emphasis in Consciousness, Health and Healing, 2016. Master of Spiritual Science, 2021, and Doctor of Spiritual Science, 2025, Peace Theological Seminary & College of Philosophy.
Educational purposes only. This article does not diagnose any condition and is not a substitute for medical care. Chiropractic care is not a treatment for anemia, thyroid disease, sleep apnea or the other medical conditions that can cause fatigue. Persistent or unexplained fatigue warrants appropriate medical evaluation. Seek prompt medical care for fatigue accompanied by chest pain, significant shortness of breath, fainting, new neurological symptoms, unexplained bleeding, or other severe or rapidly worsening symptoms. Individual results vary and no particular outcome is promised.
Ptak Family Chiropractic
We listen… We care… We get results…
Chiropractic for Adults and Children
3122 Santa Monica Blvd., Suite 102 · Santa Monica, CA 90404
310.473.7991 · ptakfamilychiropractic.com
Mon / Wed / Thurs 8:00–12:15 and 2:00–6:00 · Tues / Fri 8:00–12:00 · Sat 10:00–12:00
Almost everything people believe about stress is built on a mistake, and the mistake is in the first sentence: that the stress response is something going wrong. It isn’t. When your brain registers a challenge — or anticipates one — a great many systems shift at once. Heart rate and blood pressure change. Hormonal signaling changes. Muscle tension changes. Attention narrows. Digestion slows. Immune activity is redirected. Energy stops going toward projects with a long payoff and starts going toward the next few minutes. That is not malfunction. That is a body correctly reading its situation and reallocating accordingly. If you have ever wondered why you can carry something up a flight of stairs in an emergency that you could not carry on an ordinary Tuesday, that is the system working exactly as designed. The problem is not the response. The problem is that a response built for five minutes will run for five years if nothing tells it to stop.
The Variable Nobody Asks About
Bruce McEwen spent a career studying this and gave it a name: allostatic load. His formulation is the one I keep returning to because it identifies the actual variable — and the actual variable is not intensity. The chemistry that carries out the stress response — cortisol and the catecholamines chief among them — protects you in the short term. Over longer intervals, the same chemistry exacts a cost. Not different chemistry. The same chemistry, running longer than it was built to run. Which means the distinction that matters is not between good stress and bad stress. Nearly every conversation about stress is organized around that split, and it points in the wrong direction. The distinction that matters is between a system that switches on and off cleanly and a system that switched on and never switched off.
A hard week is not the thing. A hard week is what the response was designed for. Four years of a situation that never resolved is the thing — and people in year four rarely describe themselves as stressed, because it stopped feeling like an event and started feeling like their personality.
Why It Can Look Like Several Problems
People in that condition seldom arrive with one complaint. They arrive with a list. The shoulder, and also the sleep, and also the gut, and also the six weeks it now takes to get over a cold. That is not necessarily a coincidence, and it is not vagueness on the patient’s part. A system running an expensive process continuously has less available for everything else — repair, digestion, immune surveillance, recovery. What shows up is not always one dramatic failure but a general rise in the cost of running the body. Several things may get slightly worse at once, and none of them is bad enough on its own to explain the whole picture. This is where I have to be careful, and I want to be, because this is the exact point at which people in my profession can overreach. I cannot tell you that stress caused your shoulder problem. Nobody can. In any individual person, the honest answer is that the causal arrows cannot always be separated. Poor sleep, inactivity, financial strain, physical discomfort and physiological load can influence one another. Untangling which came first in one life is often beyond what the evidence permits. Anyone who tells you confidently that your stress caused a specific diagnosis has left the science behind, however satisfying the explanation may sound. What I can tell you is that the pattern is real, that duration matters, and that duration is the variable people often forget to ask about.
A Better Question
This changes the first question. The standard clinical opening is: What’s wrong? It is a reasonable question, and it finds a great deal. But it assumes the body has malfunctioned, and it goes looking for the broken part. If the stress response itself is not a malfunction — if it is an adaptive response to a situation that has not changed — then another question belongs alongside the first: What is this body responding to, and how long has it been responding? The second half of that question matters. In practice, I find that people can often answer it more precisely than they expected. Not stress in general. Something specific. A change in a relationship. A financial problem. An illness in the family. A difficult job. An injury. Months without adequate sleep. A responsibility that was supposed to be temporary and somehow became permanent.
Something with a beginning. And frequently, something that is still going on. The answer does not necessarily produce a treatment. What it can produce is a more accurate account of the situation, which is different from a diagnosis and sometimes just as important. A body that has been responding to something real for four years is not necessarily a body that simply “broke down.” It may be a body that has been paying attention for a very long time.
Maybe It’s Time to Ask a Different Question
If you have been dealing with recurring tension, discomfort, poor sleep or symptoms that keep returning despite repeatedly treating the symptom itself, there may be value in looking at the larger picture. Not because “stress causes everything.” It doesn’t. And not because every symptom can be explained by stress. It can’t. But because your symptoms deserve more than one question. At Ptak Family Chiropractic, we look at how your body is moving, how your nervous system is functioning, what physical demands it has been adapting to, and how long those patterns have been present. Sometimes the most useful place to begin isn’t: “How do we make this symptom go away?” It is: “Why might my body still be responding this way?”
Your Body Is Talking. Are You Listening? If something keeps coming back, keeps tightening up, or simply doesn’t make sense, talk with one of our doctors. Ask us a better question. We’ll help you look for a better answer.
PTAK FAMILY CHIROPRACTIC 3122 Santa Monica Blvd., Suite 102 · Santa Monica, CA 90404 310.473.7991 · ptakfamilychiropractic.com We Listen. We Care. We Get Results.
References McEwen BS. Protective and damaging effects of stress mediators. New England Journal of Medicine. 1998;338(3):171–179. McEwen BS, Seeman T. Protective and damaging effects of mediators of stress: elaborating and testing the concepts of allostasis and allostatic load. Annals of the New York Academy of Sciences. 1999;896:30–47. Educational purposes only. Nothing here is clinical advice for any individual, and nothing here claims that chiropractic care treats disease outside the evidence supporting a particular intervention. Persistent or worsening symptoms deserve a medical evaluation.
Maybe the muscles that feel tight aren’t the muscles that need stretching—or strengthening.
You stretch your neck. You massage it. Maybe you use heat.
It feels better.
Then a few hours later—or the next morning—it’s tight again. Why? Because sometimes the muscles that feel tight aren’t the problem. They’re the muscles working overtime.
The Problem May Be on the Other Side The muscles in the back of your neck are relatively large and powerful. They help support and control your head all day long, as do the upper trapezius muscles. But the muscles in the front of your neck—the cervical flexors—are also essential. In our clinical experience, the strength and endurance of the cervical flexor muscles are critically important to maintaining normal cervical posture and the natural lordotic curve. When those muscles become weak relative to the more powerful cervical extensors and trapezius muscles, we frequently see forward head posture and loss—or even reversal—of the normal cervical curve. Now the muscles in the back of the neck have to work even harder. They tighten. They fatigue. They ache. And what do most people do? Stretch them again. It may feel good—but it may be treating the compensation rather than correcting the imbalance.
Your Neck Is Also Talking to Your Brain There’s another piece most people never hear about. The joints in your neck are filled with sensory receptors that continually send information to your brain about position and movement. This is part of proprioception—your body’s awareness of where it is in space. Your nervous system uses that information to help coordinate posture, muscle tone and balance. So, a joint problem isn’t simply a bone or muscle problem. It is also a neurological and proprioceptive problem. When normal neck-joint movement changes, the information reaching the nervous system can change. Muscle tone and function can become unbalanced, and some muscles may begin compensating for others. That’s why we don’t look at a chronically tight neck as simply a “tight muscle.” The joints, nerves and muscles work together.
So, What Can You Actually Do? If your neck is continually tight, don’t automatically stretch what’s tight. Find out why it’s tight. We look at questions such as: ● Is your neck moving properly? ● Are the cervical flexors weak or lacking endurance? ● Is your head moving forward? ● Has your normal cervical curve changed? ● Are the muscles in the back working overtime?
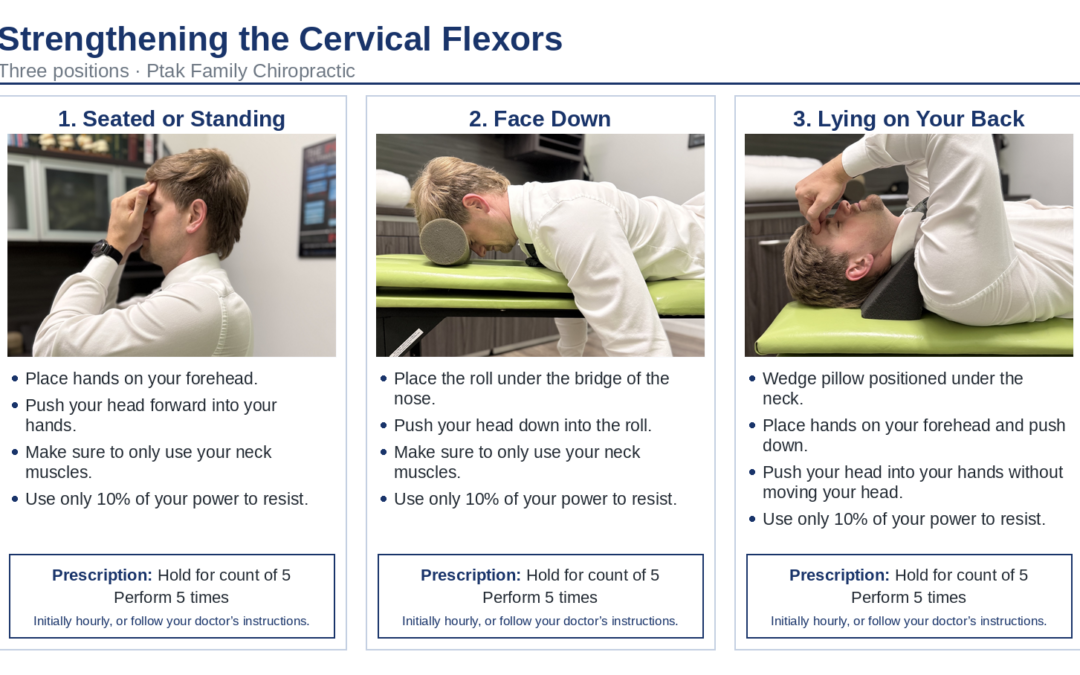
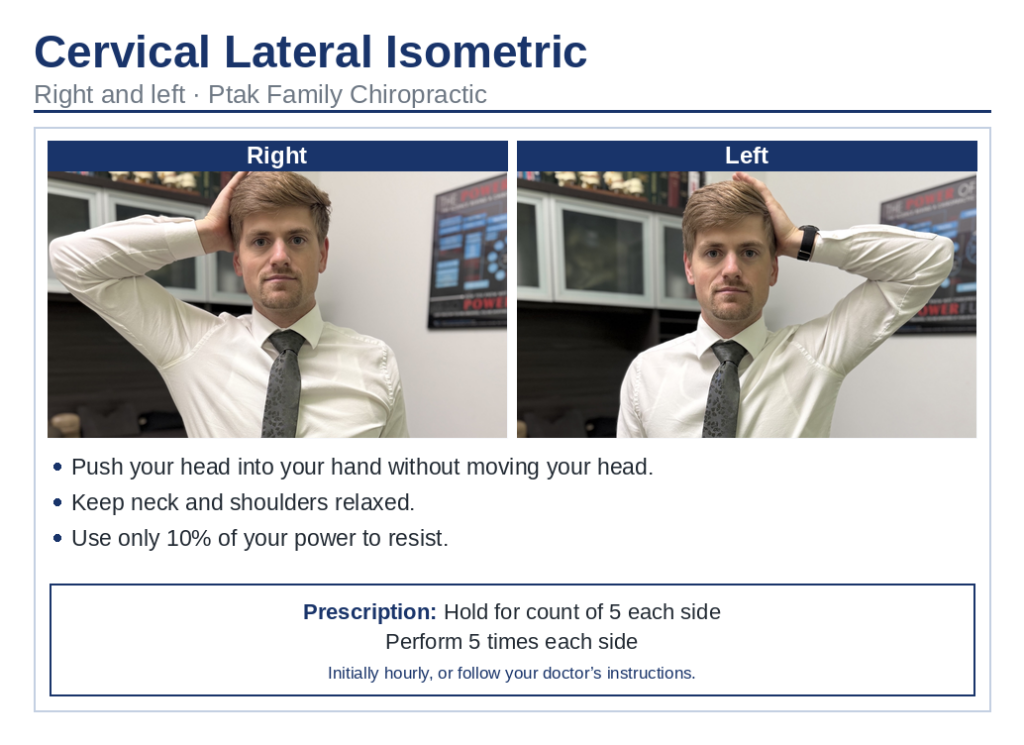
Then we address what we actually find. That may include restoring proper joint movement and alignment, activating and strengthening the cervical flexors, improving posture and proprioceptive control, and eventually strengthening the entire neck and upper back in balance.
The key is doing things in the right order.
Position first. Activate second. Strengthen third.
The Goal Isn’t a Better Stretch The goal is a neck that doesn’t need to keep tightening in the first place. So the next time you find yourself rubbing or stretching those same muscles, ask a different question: “What isn’t doing its share?” Because sometimes… Tight isn’t the problem. Tight is the compensation. Restore movement. Strengthen what’s weak. Rebalance the system.
Got Questions? Ask One of Our Doctors. Ptak Family Chiropractic 3122 Santa Monica Blvd., Suite 102 Santa Monica, CA 90404 310-473-7991
Your low back gets better. Then it comes back.Then it gets better. Then it gets WORSE.
Why?
After 40 years of treating low-back pain, we’ve learned to look beyond the place that hurts.
An injury—or physical, mental, or emotional stress—can alter spinal and pelvic joint function. And because joints are richly supplied with sensory receptors, including mechanoreceptors, a joint problem is also a nervous-system problem.
Change joint function → change neurological input → muscle function can change.
One glute may become weaker. The pelvis becomes less stable. The low-back muscles compensate by tightening, guarding and eventually going into spasm.
That can increase stress on the joints, discs and nerves—and the cycle continues.
So Why Doesn’t Exercise Always Fix It?
If one glute is weaker and you immediately exercise both sides together, the stronger side may simply keep doing more of the work.
You can exercise without correcting the imbalance.
That’s why our approach may begin differently:
Adjust and restore joint function. Identify the weaker side. Activate and strengthen that side FIRST. Restore right-to-left balance. THEN strengthen both sides together.
Sometimes this takes weeks. Sometimes months.
Crawl before you walk. Walk before you run.
After 40 years in practice, this is one of the most important missing pieces we see in people whose low-back pain improves…and then keeps coming back.
Don’t just chase the pain.
Find the imbalance. Break the cycle. Restore balance. Then build strength.
Still wondering why your low back pain keeps coming back?
Got Questions? Ask One of Our Doctors.
Ptak Family Chiropractic 3122 Santa Monica Blvd., Suite 102 Santa Monica, CA 90404 310-473-7991
For many years, obsessive-compulsive disorder (OCD) was viewed almost exclusively as a psychiatric condition treated with medication and therapy. While those treatments remain extremely important, researchers are uncovering another piece of the puzzle: in some individuals, inflammation within the brain and immune system may also contribute to OCD symptoms.
This growing understanding is helping change the conversation from simply asking, “What’s wrong with the brain?” to “What factors may be affecting how the brain is functioning?”
What Is OCD?
Obsessive-compulsive disorder (OCD) is characterized by unwanted, intrusive thoughts (obsessions) that create anxiety and repetitive behaviors or mental rituals (compulsions) performed to temporarily relieve that anxiety.
These behaviors aren’t simply habits or personality quirks. OCD can significantly interfere with work, school, relationships, and daily life.
The Brain Inflammation Connection
One of the landmark imaging studies found that people with OCD had significantly higher levels of neuroinflammation than healthy control subjects. Researchers also observed that individuals with greater inflammation often experienced more severe symptoms.
Since that original study, additional research has continued exploring how immune system activation, inflammatory signaling molecules, and overactive brain immune cells (called microglia) may influence OCD in at least a subset of patients.
Scientists are still working to determine whether inflammation causes OCD, results from OCD, or both. The relationship is likely complex and varies from person to person.
Why Inflammation Matters
Inflammation is one of the body’s natural healing responses.
When balanced, it protects us from injury and infection.
However, chronic low-grade inflammation can interfere with normal brain communication, affecting areas involved with:
Emotional regulation
Habit formation
Decision making
Anxiety
Cognitive flexibility
Many of these same brain circuits are involved in OCD.
The Brain Is Connected to the Rest of the Body
One of the biggest lessons modern neuroscience has taught us is that the brain does not function in isolation.
Sleep quality, nutrition, gut health, exercise, stress, metabolic health, hormone balance, and immune function all influence brain performance.
Although no single lifestyle factor has been proven to cure OCD, optimizing overall health may help reduce inflammatory burden and improve brain resilience.
Areas that deserve attention include:
Eating an anti-inflammatory, whole-food diet
Maintaining stable blood sugar
Regular physical activity
Prioritizing restorative sleep
Managing chronic stress
Supporting a healthy gut microbiome
Correcting nutritional deficiencies when present
These approaches are not replacements for appropriate mental health care—they are complementary strategies that support overall brain health.
Head Injuries and Brain Health
Research also continues to show that concussions and repetitive head impacts can alter brain function and increase neuroinflammation.
Anyone experiencing persistent cognitive changes, mood changes, anxiety, or obsessive symptoms after a head injury should receive a thorough neurological evaluation.
Every Person Is Different
OCD is not caused by one single factor.
For some individuals, genetics play a major role.
Others may have significant environmental influences.
Still others may have immune-related conditions, infections, developmental factors, or neurological injuries that contribute to symptoms.
This is why a comprehensive evaluation is so important. Rather than focusing only on suppressing symptoms, it’s valuable to understand what factors may be contributing to the condition in each individual.
A Whole-Person Approach
At Ptak Family Chiropractic, we recognize that the nervous system does not exist apart from the rest of the body. Brain function is influenced by movement, nutrition, sleep, stress, immune health, and overall neurological integrity.
While chiropractic care is not a treatment for OCD, improving nervous system function and addressing lifestyle factors that support brain health may be valuable components of an individual’s overall wellness plan when used alongside appropriate medical and mental health care.
If you or someone you love struggles with OCD, remember that help is available. With advances in neuroscience, we continue to gain a better understanding of the many factors that influence brain health—and that creates new opportunities for hope.
Ask the Doctor
Have questions about brain health, neuroinflammation, or whether a neurological evaluation may be appropriate for you or a loved one? We’re always happy to help you better understand your options.
Contact Ptak Family Chiropractic today to schedule a consultation. We listen… We care… We get results.