After forty years of practice, the questions I believe are worth asking while you still have a say in the answers.
Ten questions worth asking before something goes wrong: what you want to still be able to do, how steady you are, whether you are losing strength, whether your memory or mood has changed, why you take what you take, who you are still connected to, how you are sleeping, what you have quietly stopped doing, what you would struggle to get back after six weeks down, and what you are avoiding finding out. Each one includes what to do about your answer. None of them requires a symptom to begin.
Over forty years of caring for patients, I’ve learned that some of the most important questions about our health are the ones we don’t think to ask until something goes wrong.
We tend to pay attention when something hurts, when an activity becomes difficult, or when a test reveals a problem. But what about the things that change so gradually we barely notice them?
What are we no longer doing? What are we taking for granted? And what would we like to still be capable of doing ten or twenty years from now?
These are ten questions I believe are worth asking before something goes wrong.
Some are supported by established medical and public-health research. Others come directly from what I’ve observed in my patients and experienced in my own life.
All ten are questions we can begin asking ourselves today.
1. What Do I Actually Want to Be Able to Do — and Does Anyone Know?
Every other question on this list is a means to this one. Without an answer, care gets organized around whatever is loudest rather than around what you are trying to protect.
I will say this much for starting here: it is where the people who study aging start too. The framework most widely used in American geriatric care — the 4Ms, from the Institute for Healthcare Improvement and the John A. Hartford Foundation — does not begin with a disease. Its first M is What Matters: what the person in front of you actually wants to be able to do.
My answer. I want to still be practicing. I want to still be writing. I want to still be a beginner at something, which matters more than it sounds. Everything I do physically is in service of those three things.
What to ask yourself. Name one specific thing you intend to still be doing ten years from now. Not a value — an activity, with a verb in it. Then ask whether the person who looks after your health knows what it is.
2. How Steady Am I — Really?
Balance is a capacity many of us never deliberately learned to train. It is also one of the first things I check, because unsteadiness tends to be noticed late and explained away early.
There are three questions I would ask anyone over 65, and they are the same three the Centers for Disease Control and Prevention puts in front of clinicians in its fall-prevention program. Have you fallen in the past year? Do you feel unsteady when standing or walking? Do you worry about falling?
Vision and hearing belong in this question too. Both feed your balance, both are assessed in the World Health Organization’s framework for older adults, and both can go unchecked for years.
My answer. I work on balance deliberately, in a way that costs me no extra time: I stand on one leg while I brush my lower teeth, then switch legs for the upper. That is my routine, built on top of years of practice, and it is not where I would start someone who is already unsteady.
What to ask yourself. Answer those three questions honestly. Any yes is worth an examination rather than a resolution to be more careful. Start balance work on a firm floor with something solid to hold, at a level you can hold comfortably, and have someone guide the progression if you are unsteady or have fallen.
3. Am I Losing Strength — and Would I Know?
Muscle mass declines with age and strength tends to follow. The part that matters is that it is not a one-way street. Older adults gain strength when they train, and that has been shown repeatedly.
What strikes me is how few people know which direction they are moving. Nothing in an ordinary year measures it, so the change registers only when something becomes difficult.
My answer. I weight train two or three days a week and practice yoga three or four days a week. Not to be stronger than I was at 40. To keep what I have, and to know where it stands.
What to ask yourself. Pick one thing you can measure now and write it down — how many times you can stand up from a chair without using your hands, how long you can carry a loaded bag, how far you can walk before it becomes an event. None of those is a verdict on your health; they are markers you can repeat. Check one again in a few months. And if something is already limited, there is no reason to wait for the second measurement to start working on it.
4. Is My Memory or My Mood Different Than It Was a Year Ago?
This is the question people are most likely to notice privately and least likely to raise. It is also on every expert list I have seen, including the 4Ms, where it is the third M.
I raise it because some causes of changed memory or mood are treatable and some are reversible. That is not a promise about any individual. It is a reason to ask rather than to wait.
What to ask yourself. Has anything changed in how you remember, concentrate, or feel most days, compared with a year ago? Has anyone who knows you well mentioned it? If the answer to either is yes, that belongs with your physician, and it is worth raising early rather than after a year of wondering.
5. Do I Know Why I Take Each Thing I Take — and When Was It Last Reviewed?
In a 2019 national survey, 89% of adults 65 and older reported currently taking a prescription medicine, and 54% reported taking four or more. Every one of those was started for a reason. Not all of those reasons are still current, and nobody finds that out unless somebody looks.
Let me be clear about what I am not saying. This is not an argument against medication. Some conditions are not negotiable, and some of the healthiest people I know take something every day. It is an argument for knowing why.
My answer. I take no prescription or over-the-counter medications. I am not in a position to tell you why. Some of it is what I do. Some of it is luck, and the absence of a disease that would have made all of this harder.
What to ask yourself. List everything you take, including what you buy without a prescription and every supplement. Beside each one, write why. Then bring that list to the physician who prescribed them and ask which ones still need to be there. Do not stop anything on your own.
6. Who Am I Still Connected To?
I did not expect to be putting this on a list about physical health, and then I read the research.
In 2023 the U.S. Surgeon General issued an advisory naming social isolation and loneliness as independent risk factors for cardiovascular disease, dementia, depression and premature death. The meta-analysis underneath that finding associated social isolation with roughly a 29% higher likelihood of mortality, loneliness with about 26%, and living alone with about 32%.
Those are associations across populations, not predictions about any one person, and that is still a larger signal than most of what people worry about.
What to ask yourself. Name the people you would call. Then ask when you last actually did, and what you are doing to keep those relationships alive rather than assuming they will keep.
7. Am I Sleeping — and If Not, Do I Know Why?
This one is mine. It is not a named domain in the frameworks, and I think it should be.
Sleep sits underneath pain, recovery, mood, memory and balance all at once, and it is the thing I hear about last. People will describe a year of poor sleep as background rather than as a finding.
What to ask yourself. How long does it take you to fall asleep, how many times are you up, and do you wake rested? Persistent poor sleep is worth evaluating rather than absorbing. It can have identifiable and treatable causes, including some that are medical.
8. What Have I Stopped Doing — and Did I Decide To?
This question comes from watching it happen for forty years.
People rarely quit things. They stop one at a time, sensibly, for a reason that made sense that week. Something gets handed to someone else. A route gets changed to avoid the stairs. A standing arrangement quietly lapses. Together those decisions are the shape of a life getting smaller, and almost nobody notices while it is happening.
People give things up for all sorts of reasons — priorities change, money changes, someone needs caring for, an illness intervenes. But some of those decisions were made to avoid discomfort rather than after anyone examined what the discomfort was. Those are the ones worth revisiting, because they may not need to be permanent.
What to ask yourself. Name three things you did five years ago and do not do now. Then ask, for each one, whether you chose it or whether it simply happened.
9. If I Lost Six Weeks, What Wouldn’t Come Back on Its Own?
A fall, an illness, a surgery, a hospital stay. Six weeks of doing very little.
Some of what you lose in that time returns by itself. Some of it takes work, and some of it takes help. How much strength, endurance and mobility you had beforehand can make a real difference in what it takes to recover afterward — and that is built in advance, never during.
This is the question on this list I care about most, because the answer is only useful before you need it.
What to ask yourself. If you were flat for six weeks, what would be hardest to get back? Build that one now, while nothing is wrong.
10. What Am I Avoiding Finding Out?
This is the uncomfortable one, and I have saved it for last on purpose.
Most people are not failing to check. They are declining to look. There is a test they have not scheduled, a symptom they have not mentioned, a question they have not asked because they are not sure they want the answer.
I understand it. And over forty years of caring for patients and their families, I have watched it happen on a larger scale than one person’s test result.
People do tell me what they are afraid of, once they trust me enough to say it out loud, and it is never abstract. They are afraid of needing someone to bathe them, dress them, help them in the bathroom, get them in and out of bed. Of taking pills they never used to take. Of catching everything that goes around. Of giving up the things they love doing on their own — not because they decided to, but because their body or their memory stopped cooperating. Of leaving their home for somewhere they did not choose. Of becoming a burden on the people they spent a lifetime taking care of. Of running out of money before they run out of years. And of dying.
I have also watched it from the other side — families making hard decisions about caregiving, nursing homes and money, and trying to provide what someone needs without exhausting the people providing it. Watching my own parents grow older gave me another view of the same questions.
Many people never face most of that, and plenty stay independent and engaged into very old age. But these are the fears people actually carry, and the hardest questions inside them are not medical. Will I be able to stay in my home? Who will care for me if I cannot care for myself? How will we afford it? What happens when someone I love needs more help than I can give?
I have heard those questions in my office for four decades, and almost always after a crisis had already forced them.
Not knowing does not buy time. It spends it.
What to ask yourself. Two things. What is the one thing you suspect about your own health and have not had looked at? And what is the one conversation with your family you have been putting off? Each of those is a next step, with whoever is the right person for it.
What All Ten Have in Common
Not one of them requires a symptom to begin.
That is the whole point. And when medical care becomes necessary, you want people who know exactly what to do. But that care starts after the thing you were hoping to avoid.
Every question above can be answered this week, by you, with no appointment and no test. Several of the answers will point you toward a clinician, and that is what they are for.
One assignment, if you take nothing else from this article: answer question 1 and question 9. What do you intend to still be doing in ten years, and what would be hardest to get back if you lost six weeks. The gap between those two answers is your work.
I cannot promise anyone more years. I can tell you which questions are worth asking while you still have a say in the answers.
An Invitation
Whether you live in Santa Monica or are reading this from somewhere else, you are welcome at Ptak Family Chiropractic.
We’ll look at how you move, how your joints function, and what your strength, balance and neurological findings show us. What we find determines what we do — and if what you need belongs with your physician or another specialist, we’ll tell you that too.
Two of these questions are ones we can take straight into an examination — question 1 and question 8. What do you intend to still be doing in ten years, and what have you stopped doing without deciding to? Bring us those two answers. We never charge you to sit down and talk about your needs. Call Ptak Family Chiropractic at 310.473.7991 and make an appointment.
Or visit ptakfamilychiropractic.com.
Selected References
Institute for Healthcare Improvement and The John A. Hartford Foundation. Age-Friendly Health Systems: the 4Ms framework. Issue brief, March 2022.
World Health Organization. Integrated care for older people (ICOPE): guidelines on community-level interventions to manage declines in intrinsic capacity. Geneva: World Health Organization; 2017.
Sarmiento K, Lee R. The CDC’s STEADI initiative: promoting older adult health and independence through fall prevention. American Family Physician. 2017;96(4):220–221.
Holt-Lunstad J, Smith TB, Baker M, Harris T, Stephenson D. Loneliness and social isolation as risk factors for mortality: a meta-analytic review. Perspectives on Psychological Science. 2015;10(2):227–237.
Office of the Surgeon General. Our Epidemic of Loneliness and Isolation: the U.S. Surgeon General’s Advisory on the Healing Effects of Social Connection and Community. Washington, DC: U.S. Public Health Service; 2023.
Kaiser Family Foundation. Data note: prescription drugs and older adults. KFF Health Tracking Poll, February 2019.
Volpi E, Nazemi R, Fujita S. Muscle tissue changes with aging. Current Opinion in Clinical Nutrition and Metabolic Care. 2004;7(4):405–410.
World Health Organization. WHO Guidelines on Physical Activity and Sedentary Behaviour. Geneva: World Health Organization; 2020.
Sherrington C, Fairhall NJ, Wallbank GK, et al. Exercise for preventing falls in older people living in the community. Cochrane Database of Systematic Reviews. 2019;1:CD012424.
About the author. Dr. Jeffrey Ptak, DC, DSS, MSS, MA, founded Ptak Family Chiropractic in Santa Monica and has practiced since 1986. He is the author of the forthcoming book It’s Like You Never Left, to be published by Indigo River Publishing.
Educational information only; not a diagnosis or a substitute for individualized care. The personal practices described here are one person’s choices and are not recommendations or treatment for any condition. Do not start, stop or change any prescribed or over-the-counter medication or supplement without consulting the prescribing physician. Begin new physical activity at a level appropriate to your current health, and practice balance only with stable support and, where appropriate, supervision. Seek prompt medical evaluation for new or progressive weakness, persistent numbness, unexplained weight loss, fever, night pain that consistently wakes you, or new changes in memory, mood or speech. Seek emergency care immediately for sudden loss of balance with slurred speech, facial drooping, one-sided weakness, double vision or a severe sudden headache.
Ptak Family Chiropractic
We listen… We care… We get results…
Chiropractic for Adults and Children
3122 Santa Monica Blvd., Suite 102 · Santa Monica, CA 90404
310.473.7991 · ptakfamilychiropractic.com
Mon / Wed / Thurs 8:00–12:15 and 2:00–6:00 · Tues / Fri 8:00–12:00 · Sat 10:00–12:00
Which fingers go numb tells us where to start looking and it may not be your wrist.
Jeffrey Ptak, DC, DSS, MSS, MA
Nighttime hand numbness does not automatically mean carpal tunnel. The first useful question is much simpler: which fingers? The classic median-nerve pattern involves the thumb, index and middle fingers and part of the ring finger. A different pattern points somewhere else along the nerve pathway and that pathway begins at your neck.
You wake up in the middle of the night and your hand is numb or tingling.
You shake it. Change positions. Maybe straighten your wrist or move your arm. It settles down, you go back to sleep — and then it happens again the next night.
It happens twice a week. Then four. Then you notice it while driving or holding your phone.
Eventually someone says, “Probably carpal tunnel.”
Maybe. But nighttime hand numbness does not automatically mean carpal tunnel. The first useful question is much simpler:
Which fingers?
Start With the Fingers
Carpal tunnel syndrome involves compression of the median nerve at the wrist. Its classic sensory pattern involves the thumb, index and middle fingers and part of the ring finger. Symptoms commonly wake people at night, and shaking the hand may temporarily relieve them.
If the little finger and the other side of the ring finger are involved, we begin thinking about a different nerve pathway, including the ulnar nerve. And symptoms that extend into the arm, change with neck position, or occur with weakness may point us toward still another part of the pathway.
You do not need to interpret the pattern. Just notice it.
And why at night? Because of how we sleep. Many people spend hours with a wrist bent, an elbow fully flexed, or a hand tucked beneath a pillow or under their own body — positions nobody would hold voluntarily while awake. Sustained wrist flexion or extension can provoke median-nerve symptoms, and a fully bent elbow can do the same for the ulnar nerve.
Which is also why shaking your hand helps. You have changed the position.
Which fingers and where exactly does the numbness stop? If you can remember, what position were your arm, elbow and wrist in when it happened?
Your Hand Is Where You Feel It. That Doesn’t Mean It’s Where the Problem Begins.
The nerves supplying your hand travel through a pathway that includes the neck and upper extremity before reaching the fingers. A nerve can be irritated or compressed at different places along that route.
That is why examining only the wrist can miss important information.
A good examination should ask a more useful question:
Where along the pathway can we find something that relates to the symptoms you actually feel?
Let’s Examine the Whole Pathway
At Ptak Family Chiropractic in Santa Monica, checking potential areas of nerve irritation or entrapment is a routine part of our examination when someone comes in with hand numbness or tingling.
Depending on your symptoms, we may examine the neck, clavicle region, shoulder, arm, elbow, wrist and hand.
But we are not simply looking for something abnormal. We are looking for findings that relate to your symptoms.
Does a particular position reproduce the numbness? Does changing the position reduce it? Does loading or releasing part of the nerve pathway change what you feel? Is there a corresponding change in strength, sensation or reflexes?
Specific wrist tests may be useful when carpal tunnel is suspected, but no single maneuver should replace the history and the rest of the examination. Current clinical guidance supports examining the entire upper extremity — including the neck, shoulder, elbow and wrist — because other problems can resemble carpal tunnel syndrome.
Now we have more than “my hand falls asleep.” We have a pattern — and findings we can relate to it.
If Someone Recommends a Night Splint
Night splinting is a common and reasonable first step when carpal tunnel is suspected. But the position matters, and it is easy to buy the wrong one.
Pressure inside the carpal tunnel is lowest with the wrist in neutral. Both bending and extending the wrist raise it. A cock-up splint holds the wrist in roughly twenty degrees of extension — and in trials comparing the two, neutral splints gave better symptom relief than splints set at twenty degrees of extension.
Both styles are widely sold at similar prices, so if a splint is recommended, the neutral one is worth asking for.
Two other things worth knowing. Relief, when it comes, tends to appear within the first couple of weeks rather than building slowly over months. And a splint is not a diagnosis it does nothing for an ulnar nerve irritated at the elbow, and nothing for a nerve root irritated in the neck.
What We Find Determines What We Do
If the findings suggest something within our scope that we can help change, we will explain what we found and what we can do.
If the pattern suggests that nerve-conduction testing, medical evaluation or another specialist is appropriate, we will tell you and refer you.
The goal is not to assume carpal tunnel. The goal is to determine where the symptoms may be coming from and what, if anything, can be done about them.
When It Shouldn’t Wait
Most nighttime hand numbness is not an emergency. Some findings change that.
Arrange prompt evaluation for weakness rather than numbness alone dropping things, difficulty with buttons, keys or jar lids; visible thinning of the muscle at the base of the thumb; numbness that has become constant rather than intermittent; numbness in both hands and both feet; or symptoms following an injury.
And seek urgent care for sudden numbness or weakness in a hand or arm accompanied by facial droop, difficulty speaking, or weakness elsewhere.
Numbness that comes and goes is generally easier to help than numbness that has become permanent, which is why weakness and muscle wasting move the timeline.
Tonight, Notice One Thing
If your hand wakes you tonight, you do not need to diagnose yourself.
Notice which fingers go numb.
If you can, notice the position of your arm, elbow or wrist too.
Then let us do the rest.
If your hands keep going numb while you sleep, let’s check you. We never charge you to sit down and talk about your needs. Call Ptak Family Chiropractic at 310.473.7991 and make an appointment.
You do not need to decide whether it is carpal tunnel before you come in. That is what the examination is for.
Selected References
American Academy of Orthopaedic Surgeons. Management of Carpal Tunnel Syndrome: Evidence-Based Clinical Practice Guideline. 2024.
Wipperman J, Goerl K. Carpal Tunnel Syndrome: Diagnosis and Management. American Family Physician. 2016;94(12):993–999.
LeBlanc KE, Cestia W. Carpal Tunnel Syndrome. American Family Physician. 2011;83(8):952–958.
Burke DT et al. Splinting for carpal tunnel syndrome: in search of the optimal angle. Archives of Physical Medicine and Rehabilitation, 1994.
Beutler A, Stephens M. Letter: Best Treatment Approaches for Carpal Tunnel Syndrome — neutral versus cock-up splints. American Family Physician, 2012.
About the author. Dr. Jeffrey Ptak, DC, DSS, MSS, MA, is the founder of Ptak Family Chiropractic in Santa Monica, where he has practiced since 1986. His postgraduate study includes Chiropractic Functional Neurology through the Carrick Institute and advanced training through the International Association of Functional Neurology and Rehabilitation. He is the author of the forthcoming book It’s Like You Never Left, to be published by Indigo River Publishing.
Educational purposes only. This article does not diagnose any condition and is not a substitute for medical care. Seek urgent care for sudden numbness or weakness in an arm or hand accompanied by facial droop, difficulty speaking or weakness elsewhere. Arrange prompt evaluation for weakness, visible muscle thinning at the base of the thumb, constant rather than intermittent numbness, numbness in both hands and feet, or symptoms following injury. Individual results vary and no particular outcome is promised.
Ptak Family Chiropractic
We listen… We care… We get results…
Chiropractic for Adults and Children
3122 Santa Monica Blvd., Suite 102 · Santa Monica, CA 90404
310.473.7991 · ptakfamilychiropractic.com
Mon / Wed / Thurs 8:00–12:15 and 2:00–6:00 · Tues / Fri 8:00–12:00 · Sat 10:00–12:00
Don’t just tell me you wake up stiff. Tell me how long it takes to loosen up.
Almost everyone is somewhat stiff on waking. The useful information is how long it takes to loosen up, where you feel it, and whether moving helps. That number won’t diagnose you, but it tells us a great deal about what to examine and it helps separate a mechanical problem we may be able to change from a pattern that needs medical evaluation.
You get out of bed and everything needs a minute.
Your back is stiff. Your neck doesn’t want to turn. Your hips need a few steps before they cooperate.
Then you move around, shower, make coffee and somewhere along the way you loosen up.
Tomorrow morning, don’t just notice it.
Time it.
Five minutes? Twenty? Forty-five? More than an hour?
That number won’t diagnose you. But it can tell us a great deal about what to examine next.
What the Time Tells Us
Stiffness that eases within a few minutes of moving is a common pattern in mechanical and age-related joint problems. The joint has been still for seven or eight hours. It needs input, and movement provides it.
Stiffness that lasts considerably longer, involves several joints, appears on both sides, or comes with swelling means something different. Prolonged morning stiffness is one of the features clinicians look for in inflammatory conditions such as rheumatoid arthritis, polymyalgia rheumatica, and inflammatory back conditions like ankylosing spondylitis.
Roughly half an hour to an hour is the figure often quoted. Treat it as a clue rather than a dividing line — a useful signal, not a diagnosis.
Then notice what makes it better. Mechanical stiffness usually rewards movement. Inflammatory stiffness often improves with movement and worsens with rest, which sounds the same until you notice it also lasts far longer and rarely travels alone.
As for the mattress: it is the first thing most people change and occasionally it helps, but the position may matter more than the surface — a joint held near the end of its range for seven hours is likely to have an opinion about it in the morning.
When the Pattern Needs Medical Evaluation
Have this properly evaluated rather than pushing through it if:
the stiffness regularly lasts longer than an hour, or several joints are involved, especially symmetrically or in the small joints of the hands and feet
joints are swollen, warm or visibly red
you are over fifty and have developed sudden, severe stiffness and aching in the shoulders and hips, particularly with difficulty raising your arms
there is new headache, scalp tenderness, jaw pain with chewing, or any change in vision — in an older adult that combination needs urgent medical attention
there is fever, night sweats or unexplained weight loss
back pain wakes you in the second half of the night and improves with movement rather than rest, especially if it began before age forty-five
there is progressive weakness or numbness, or any change in bladder or bowel control
Widespread pain with poor sleep and fatigue also deserves proper evaluation rather than a shrug — fibromyalgia and related conditions are recognized medical diagnoses.
None of that is meant to frighten you. It is meant to make sure the right person is looking at the right thing.
What We Can Actually Do
At Ptak Family Chiropractic in Santa Monica, we don’t treat morning stiffness as though everyone has the same problem.
We examine where you’re stiff, which movements are restricted, whether movement reproduces or relieves it, and whether weakness, poor mobility or the way you’re loading an area is contributing.
What we find determines what we do.
If a joint isn’t moving well, chiropractic care may help restore movement. If muscles are weak or lack endurance, strengthening becomes part of the solution. If the problem is how you’re sleeping, sitting or repeatedly loading the area, we work on changing that too.
The goal isn’t simply to make you feel looser for an hour.
It’s to identify what is making you stiff every morning and determine what can actually be changed.
And if the pattern suggests inflammatory arthritis or another medical condition rather than a mechanical problem, we’ll tell you and help direct you to the appropriate specialist.
“I Guess This Is Just My Age”
Recovery does change over a lifetime. But age is not a diagnosis. Plenty of seventy-year-olds get out of bed easily, and plenty of thirty-five-year-olds don’t.
If your body now needs twenty-five minutes and a hot shower before it will cooperate, something specific has changed. Strength. Range of motion. Sleep. Load. Something.
“Age” is the word we reach for when we have stopped looking for the specific thing.
Bring Us the Number
Tomorrow morning, time your stiffness.
Where is it?
How long before you loosen up?
What makes it better?
Bring us those answers. They give us something useful to examine.
Come and talk with us. We never charge you to sit down and talk about your needs. Bring the three answers above, and note what position you wake up in. We’ll examine what is ours to examine and tell you honestly whether this looks like something we can change — and if several joints are involved, or they’re swelling, or the stiffness lasts more than an hour, we’ll tell you that belongs with your physician and why.
A little stiffness on waking is ordinary. A morning built entirely around getting your body to work is not.
About the author. Dr. Jeffrey Ptak, DC, DSS, MSS, MA, is the founder of Ptak Family Chiropractic in Santa Monica, where he has practiced since 1986. His postgraduate study includes Chiropractic Functional Neurology through the Carrick Institute and advanced training through the International Association of Functional Neurology and Rehabilitation. He is the author of the forthcoming book It’s Like You Never Left, to be published by Indigo River Publishing.
Educational purposes only. This article does not diagnose any condition and is not a substitute for medical care. Morning stiffness and body aching have many possible causes, some requiring medical diagnosis and treatment. Prolonged stiffness, joint swelling, fever, unexplained weight loss, new neurological symptoms, or severe or rapidly worsening symptoms warrant prompt medical evaluation. Individual results vary and no particular outcome is promised.
Ptak Family Chiropractic
We listen… We care… We get results…
Chiropractic for Adults and Children
3122 Santa Monica Blvd., Suite 102 · Santa Monica, CA 90404
310.473.7991 · ptakfamilychiropractic.com
Mon / Wed / Thurs 8:00–12:15 and 2:00–6:00 · Tues / Fri 8:00–12:00 · Sat 10:00–12:00
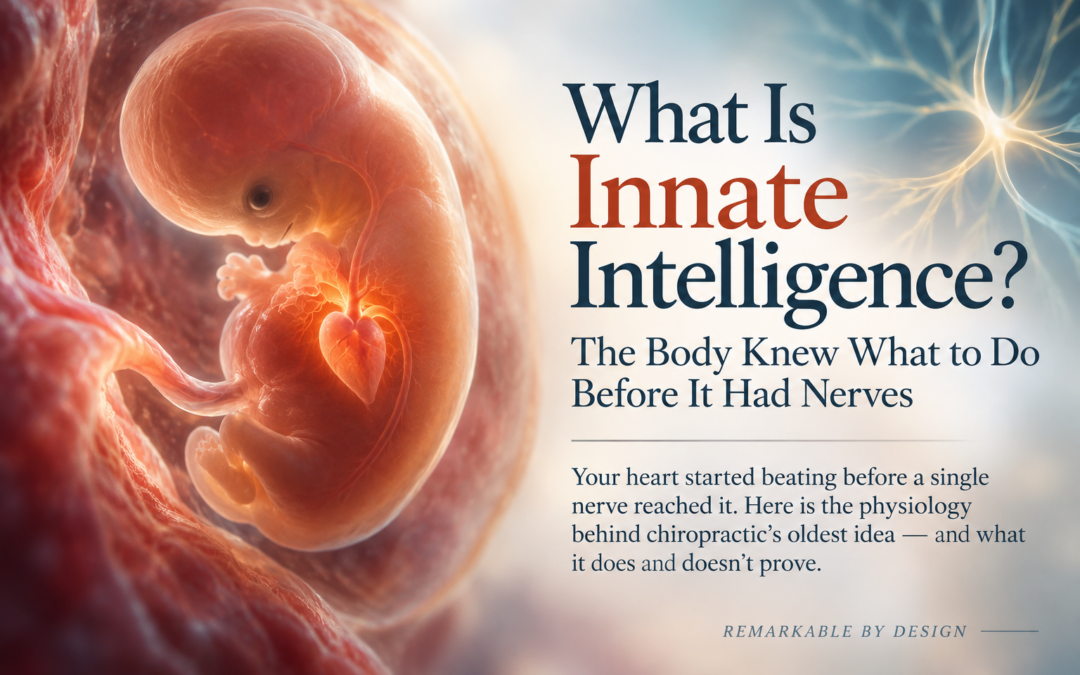
Your heart started beating before a single nerve reached it. Here is the physiology behind chiropractic’s oldest idea — and what it does and doesn’t prove. Jeffrey Ptak, DC, DSS, MSS, MA
Yesterday marked 131 years since the day chiropractic traces its beginning, September 18, 1895. So today seems like the right time to talk about one of the oldest — and most misunderstood — ideas in chiropractic: innate intelligence.
Innate intelligence is chiropractic’s name for the body’s built-in capacity to organize, regulate and repair itself. It is a philosophical idea, not a laboratory measurement. But the physiology it points to is real: the body begins organizing itself before the nervous system exists, and once the nervous system is in place, it becomes woven into how the body regulates, heals and defends itself.
You cut your finger. You do nothing. Within minutes the bleeding stops. Within days the gap closes. Within weeks you can barely find the scar. You didn’t tell your platelets where to go. You didn’t schedule the inflammation or order new skin. Something organized all of it without asking you. Chiropractic has had a name for that something for more than a century.
A Word Chiropractic Has Used Since 1910
D.D. Palmer gave the first chiropractic adjustment in Davenport, Iowa, in 1895. Fifteen years later he wrote about “innate intelligence”: the organizing wisdom by which a living body maintains and heals itself. Chiropractors have repeated a shorter version ever since: the power that made the body heals the body. Palmer meant it in an explicitly spiritual sense. Modern chiropractic historians, most notably Simon Senzon, have argued that today’s systems biology offers another way to understand his idea of a body that organizes itself. Medicine arrived at the same observation by a different road. In 1932 the Harvard physiologist Walter Cannon published The Wisdom of the Body and gave the body’s self- regulation a scientific name: homeostasis.
Innate intelligence is a philosophy. You can’t put it under a microscope. But you can test the physiology it points to, and that physiology is remarkable.
Your Heart Started Before Its Nerves Did
About three to four weeks after conception, the human heart begins to beat. At that stage it is a simple tube of cells. No nerve directs it. The rhythm is generated by the heart muscle itself, in specialized pacemaker cells that fire on their own. The nerves that will later speed the heart up and slow it down arrive afterward. Organization comes first. The body does not wait for wiring before it begins to live.
Then the Nerves Take Over the Fine Tuning
A transplanted heart shows the other half of the story. When a heart is transplanted, the nerves connecting it to the brain and spinal cord are cut. The heart still beats. But it no longer beats the same way. Its resting rate is typically faster, because the vagus nerve is no longer slowing it. During exercise it can only speed up slowly, waiting for adrenaline to arrive through the bloodstream instead of receiving an immediate nerve signal. Over months and years some nerve fibers grow back, usually incompletely. Life continues without the connection. Regulation suffers without it.
The Salamander’s Lesson
Salamanders can regrow a lost limb. In 1823 the Scottish physician Tweedy John Todd noticed something about that ability: if he cut the nerves to the limb, it didn’t grow back. In the 1940s and 1950s the biologist Marcus Singer showed that regeneration requires a threshold amount of nerve supply. Then researchers found a twist. Salamanders raised so that their limbs never received nerves can regenerate those limbs without them. It is only after a limb has been innervated that its regeneration comes to depend on the nerve. That may be the clearest picture of innate intelligence in biology. The capacity to organize is present from the beginning. Once the nervous system arrives, the body builds it into the way it maintains and repairs itself — and from then on, it relies on it.
The Nervous System Is Woven Into Healing
This isn’t limited to salamanders. Over the past twenty-five years, research has shown the nervous system taking part in processes once thought to run entirely on their own.
Wound healing. In mice, removing a group of sensory nerve cells impaired both skin wound repair and muscle regeneration. Those nerves help steer immune cells from the inflammatory phase of healing into the repair phase.
Inflammation. The vagus nerve senses inflammation and signals back to restrain it in real time, a circuit its discoverer named the inflammatory reflex.
Bone. In mice, a signal from the brain acting through the sympathetic nervous system helps regulate how much bone is formed.
Blood stem cells. Also in mice, sympathetic nerves in the bone marrow release blood- forming stem cells into circulation on a daily rhythm.
Digestion. The gut contains its own nervous system, with more neurons than the spinal cord. An isolated segment of intestine can still move its contents along. The pattern repeats. Cells can do a great deal on their own. But the nervous system is involved in coordinating, timing and tuning what they do.
What These Examples Show — and What They Don’t
These findings show that the body is self-organizing, and that the nervous system is deeply involved in regulation, repair and defense. They do not prove that a chiropractic adjustment will improve any one of those processes in any one person. Much of the research above was done in animals, and research on how spinal care influences these systems is still early. Anyone who tells you otherwise is claiming more than the evidence shows. What they do support is the premise chiropractic was built on: how well the nervous system is working matters to how well the body is working.
Where Chiropractic Fits
Your spine houses and protects the spinal cord, and its joints are richly supplied with sensory receptors that report position and movement to your nervous system, continuously. The chiropractic premise is that when spinal joints aren’t moving well, the information the nervous system receives changes, and so can the way it responds. Research has begun to look at this directly. In one study, people with recurring neck problems showed measurable changes in how the brain processed sensory input after a cervical adjustment, changes that lasted about twenty minutes and did not occur in a control group.
That’s a beginning, not a final answer. But it points in the direction chiropractic has always pointed. After forty years in practice, this is what I believe: whatever else is going on in your body, you are better off with a nervous system working without interference than with it. That is not a promise about any particular condition. It is the reason I examine the nervous system in every patient who walks through my door. Good regulation isn’t simply more drive. The nervous system needs a gas pedal and a brake, and it needs the signals to both to come through clearly.
Let’s Check You
At Ptak Family Chiropractic in Santa Monica, we examine how your spine moves and how your nervous system is functioning: reflexes, sensation, strength, balance and coordination, along with the joints and muscles involved in whatever brought you in. What we find determines what we do. If we find something we can help change, we’ll show you what it is and what we plan to do about it. If it belongs with your physician or another specialist, we’ll tell you that too.
If you want to know how well your nervous system is doing its job, let’s check you. We never charge you to sit down and talk about your needs. Call Ptak Family Chiropractic at 310.473.7991 and make an appointment.
You don’t need to believe in innate intelligence before you come in. That’s what the examination is for.
Selected References
Palmer DD. The Science, Art and Philosophy of Chiropractic (The Chiropractor’s Adjuster). Portland Printing House; 1910.Cannon WB. The Wisdom of the Body. W.W. Norton; 1932. Senzon SA. Constructing a philosophy of chiropractic: evolving worldviews and premodern roots. Journal of Chiropractic Humanities. 2011;18(1). Wenban AB, Denis FL. Innate intelligence in the philosophy of chiropractic: a comparative analysis. Journal of Contemporary Chiropractic. 2026;9(1):185–206. Männer J. When does the human embryonic heart start beating? A review of contemporary and historical sources of knowledge about the onset of blood circulation in man. Journal of Cardiovascular Development and Disease. 2022;9(6):187.
Kumar A, Brockes JP. Nerve dependence in tissue, organ, and appendage regeneration. Trends in Neurosciences. 2012;35(11):691–699. Lu YZ et al. CGRP sensory neurons promote tissue healing via neutrophils and macrophages. Nature. 2024;628:604–611. Tracey KJ. The inflammatory reflex. Nature. 2002;420:853–859. Takeda S et al. Leptin regulates bone formation via the sympathetic nervous system. Cell. 2002;111(3):305–317. Méndez-Ferrer S, Lucas D, Battista M, Frenette PS. Haematopoietic stem cell release is regulated by circadian oscillations. Nature. 2008;452:442–447. Purves D et al., eds. Neuroscience. 2nd ed. Sinauer Associates; 2001. The Enteric Nervous System. Haavik-Taylor H, Murphy B. Cervical spine manipulation alters sensorimotor integration: a somatosensory evoked potential study. Clinical Neurophysiology. 2007;118(2):391–402.
About the author. Dr. Jeffrey Ptak, DC, DSS, MSS, MA, is the founder of Ptak Family Chiropractic in Santa Monica, where he has practiced since 1986. His postgraduate study includes Chiropractic Functional Neurology through the Carrick Institute and advanced training through the International Association of Functional Neurology and Rehabilitation. He is the author of the forthcoming book It’s Like You Never Left, to be published by Indigo River Publishing.
Educational purposes only. This article describes a philosophy of health and summarizes published research; it does not diagnose any condition, is not a substitute for medical care, and does not claim that chiropractic care treats or cures any disease. Several studies described were conducted in animals. Do not start, stop or change any prescribed treatment without consulting your physician. Individual results vary and no particular outcome is promised.
Ptak Family Chiropractic We listen… We care… We get results… Chiropractic for Adults and Children
3122 Santa Monica Blvd., Suite 102 · Santa Monica, CA 90404 310.473.7991 · ptakfamilychiropractic.com
Mon / Wed / Thurs 8:00–12:15 and 2:00–6:00 · Tues / Fri 8:00–12:00 · Sat 10:00–12:00
Almost everything people believe about stress is built on a mistake, and the mistake is in the first sentence: that the stress response is something going wrong. It isn’t. When your brain registers a challenge — or anticipates one — a great many systems shift at once. Heart rate and blood pressure change. Hormonal signaling changes. Muscle tension changes. Attention narrows. Digestion slows. Immune activity is redirected. Energy stops going toward projects with a long payoff and starts going toward the next few minutes. That is not malfunction. That is a body correctly reading its situation and reallocating accordingly. If you have ever wondered why you can carry something up a flight of stairs in an emergency that you could not carry on an ordinary Tuesday, that is the system working exactly as designed. The problem is not the response. The problem is that a response built for five minutes will run for five years if nothing tells it to stop.
The Variable Nobody Asks About
Bruce McEwen spent a career studying this and gave it a name: allostatic load. His formulation is the one I keep returning to because it identifies the actual variable — and the actual variable is not intensity. The chemistry that carries out the stress response — cortisol and the catecholamines chief among them — protects you in the short term. Over longer intervals, the same chemistry exacts a cost. Not different chemistry. The same chemistry, running longer than it was built to run. Which means the distinction that matters is not between good stress and bad stress. Nearly every conversation about stress is organized around that split, and it points in the wrong direction. The distinction that matters is between a system that switches on and off cleanly and a system that switched on and never switched off.
A hard week is not the thing. A hard week is what the response was designed for. Four years of a situation that never resolved is the thing — and people in year four rarely describe themselves as stressed, because it stopped feeling like an event and started feeling like their personality.
Why It Can Look Like Several Problems
People in that condition seldom arrive with one complaint. They arrive with a list. The shoulder, and also the sleep, and also the gut, and also the six weeks it now takes to get over a cold. That is not necessarily a coincidence, and it is not vagueness on the patient’s part. A system running an expensive process continuously has less available for everything else — repair, digestion, immune surveillance, recovery. What shows up is not always one dramatic failure but a general rise in the cost of running the body. Several things may get slightly worse at once, and none of them is bad enough on its own to explain the whole picture. This is where I have to be careful, and I want to be, because this is the exact point at which people in my profession can overreach. I cannot tell you that stress caused your shoulder problem. Nobody can. In any individual person, the honest answer is that the causal arrows cannot always be separated. Poor sleep, inactivity, financial strain, physical discomfort and physiological load can influence one another. Untangling which came first in one life is often beyond what the evidence permits. Anyone who tells you confidently that your stress caused a specific diagnosis has left the science behind, however satisfying the explanation may sound. What I can tell you is that the pattern is real, that duration matters, and that duration is the variable people often forget to ask about.
A Better Question
This changes the first question. The standard clinical opening is: What’s wrong? It is a reasonable question, and it finds a great deal. But it assumes the body has malfunctioned, and it goes looking for the broken part. If the stress response itself is not a malfunction — if it is an adaptive response to a situation that has not changed — then another question belongs alongside the first: What is this body responding to, and how long has it been responding? The second half of that question matters. In practice, I find that people can often answer it more precisely than they expected. Not stress in general. Something specific. A change in a relationship. A financial problem. An illness in the family. A difficult job. An injury. Months without adequate sleep. A responsibility that was supposed to be temporary and somehow became permanent.
Something with a beginning. And frequently, something that is still going on. The answer does not necessarily produce a treatment. What it can produce is a more accurate account of the situation, which is different from a diagnosis and sometimes just as important. A body that has been responding to something real for four years is not necessarily a body that simply “broke down.” It may be a body that has been paying attention for a very long time.
Maybe It’s Time to Ask a Different Question
If you have been dealing with recurring tension, discomfort, poor sleep or symptoms that keep returning despite repeatedly treating the symptom itself, there may be value in looking at the larger picture. Not because “stress causes everything.” It doesn’t. And not because every symptom can be explained by stress. It can’t. But because your symptoms deserve more than one question. At Ptak Family Chiropractic, we look at how your body is moving, how your nervous system is functioning, what physical demands it has been adapting to, and how long those patterns have been present. Sometimes the most useful place to begin isn’t: “How do we make this symptom go away?” It is: “Why might my body still be responding this way?”
Your Body Is Talking. Are You Listening? If something keeps coming back, keeps tightening up, or simply doesn’t make sense, talk with one of our doctors. Ask us a better question. We’ll help you look for a better answer.
PTAK FAMILY CHIROPRACTIC 3122 Santa Monica Blvd., Suite 102 · Santa Monica, CA 90404 310.473.7991 · ptakfamilychiropractic.com We Listen. We Care. We Get Results.
References McEwen BS. Protective and damaging effects of stress mediators. New England Journal of Medicine. 1998;338(3):171–179. McEwen BS, Seeman T. Protective and damaging effects of mediators of stress: elaborating and testing the concepts of allostasis and allostatic load. Annals of the New York Academy of Sciences. 1999;896:30–47. Educational purposes only. Nothing here is clinical advice for any individual, and nothing here claims that chiropractic care treats disease outside the evidence supporting a particular intervention. Persistent or worsening symptoms deserve a medical evaluation.
Maybe the muscles that feel tight aren’t the muscles that need stretching—or strengthening.
You stretch your neck. You massage it. Maybe you use heat.
It feels better.
Then a few hours later—or the next morning—it’s tight again. Why? Because sometimes the muscles that feel tight aren’t the problem. They’re the muscles working overtime.
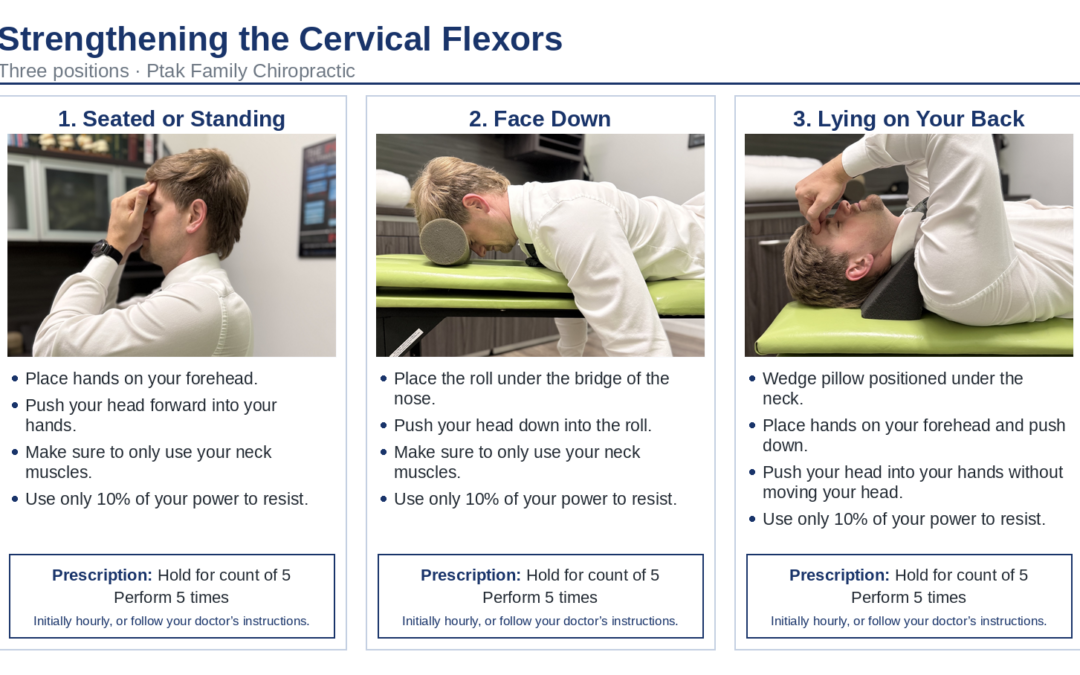
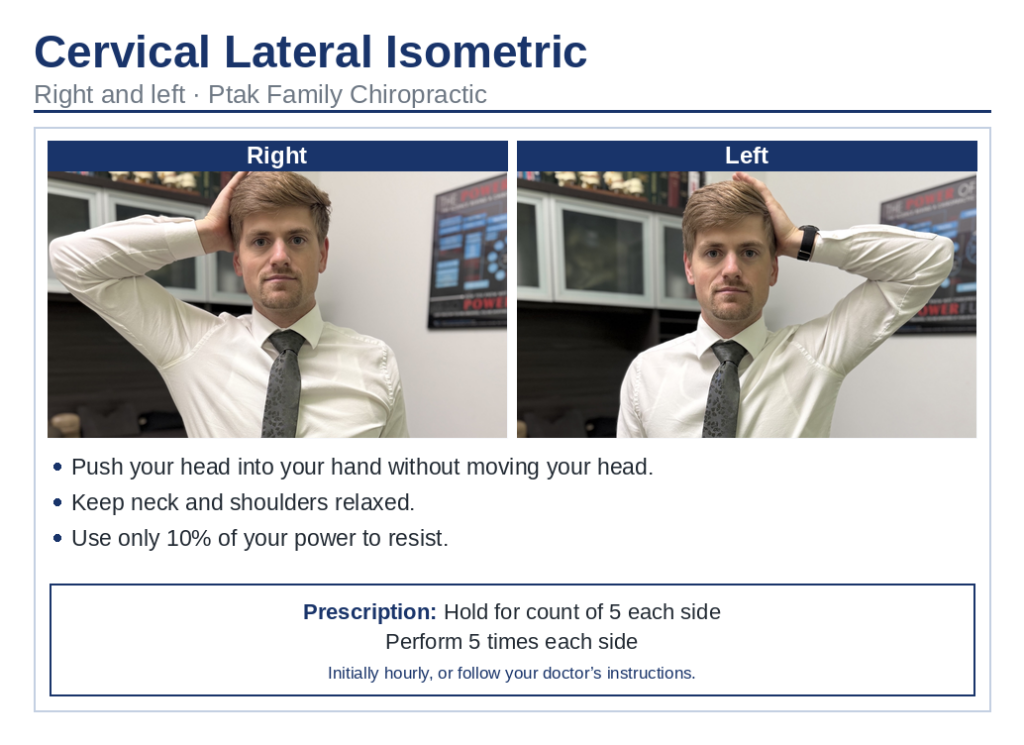
The Problem May Be on the Other Side The muscles in the back of your neck are relatively large and powerful. They help support and control your head all day long, as do the upper trapezius muscles. But the muscles in the front of your neck—the cervical flexors—are also essential. In our clinical experience, the strength and endurance of the cervical flexor muscles are critically important to maintaining normal cervical posture and the natural lordotic curve. When those muscles become weak relative to the more powerful cervical extensors and trapezius muscles, we frequently see forward head posture and loss—or even reversal—of the normal cervical curve. Now the muscles in the back of the neck have to work even harder. They tighten. They fatigue. They ache. And what do most people do? Stretch them again. It may feel good—but it may be treating the compensation rather than correcting the imbalance.
Your Neck Is Also Talking to Your Brain There’s another piece most people never hear about. The joints in your neck are filled with sensory receptors that continually send information to your brain about position and movement. This is part of proprioception—your body’s awareness of where it is in space. Your nervous system uses that information to help coordinate posture, muscle tone and balance. So, a joint problem isn’t simply a bone or muscle problem. It is also a neurological and proprioceptive problem. When normal neck-joint movement changes, the information reaching the nervous system can change. Muscle tone and function can become unbalanced, and some muscles may begin compensating for others. That’s why we don’t look at a chronically tight neck as simply a “tight muscle.” The joints, nerves and muscles work together.
So, What Can You Actually Do? If your neck is continually tight, don’t automatically stretch what’s tight. Find out why it’s tight. We look at questions such as: ● Is your neck moving properly? ● Are the cervical flexors weak or lacking endurance? ● Is your head moving forward? ● Has your normal cervical curve changed? ● Are the muscles in the back working overtime?
Then we address what we actually find. That may include restoring proper joint movement and alignment, activating and strengthening the cervical flexors, improving posture and proprioceptive control, and eventually strengthening the entire neck and upper back in balance.
The key is doing things in the right order.
Position first. Activate second. Strengthen third.
The Goal Isn’t a Better Stretch The goal is a neck that doesn’t need to keep tightening in the first place. So the next time you find yourself rubbing or stretching those same muscles, ask a different question: “What isn’t doing its share?” Because sometimes… Tight isn’t the problem. Tight is the compensation. Restore movement. Strengthen what’s weak. Rebalance the system.
Got Questions? Ask One of Our Doctors. Ptak Family Chiropractic 3122 Santa Monica Blvd., Suite 102 Santa Monica, CA 90404 310-473-7991